
AIMS Journal, 2025, Vol 37, No 2
The AIMS PIMS (Physiology Informed Maternity Services) team discusses optimal (delayed or deferred) cord clamping - an important part of physiological birth, providing the baby with its full volume of stem-cell and oxygen-rich blood.
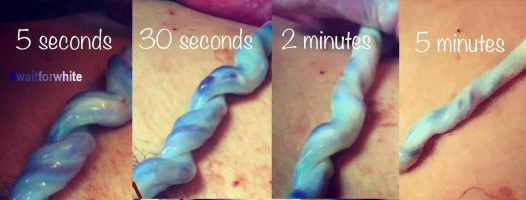
Photo by Kimm Sun, www.waitforwhite.com
It is widely known that the placenta carries out many essential functions during pregnancy, providing oxygen-rich blood and nutrients to the foetus through the umbilical cord. What isn’t so well known is that after birth the placenta and umbilical cord still carry out these vital functions for a short time, transferring blood to the baby through the umbilical vein inside the cord.
This blood, which midwives and doctors often call ‘cord blood’, is actually a vital part of the baby’s circulation. It can be up to 300 ml in volume, making up to 30-40% of the baby’s total volume of blood.[1], [2], [3], [4] Clamping and cutting the cord immediately after birth was widely introduced into hospital protocols in the UK in the 1960s, as part of a package of measures called ‘active management’ of the third stage of labour, soon becoming routine. Combined with giving oxytocic drugs immediately after birth, it was thought these practices would reduce the risk of postpartum haemorrhage for women. There were also concerns that giving drugs to prevent haemorrhage could cause the placenta to be retained or force ‘too much blood’ into the baby.[5] However, there is no evidence that carrying out immediate cord clamping alone, depriving the baby of this blood, reduces the chances of postpartum haemorrhage.[6]

Image by Lyticia Freshwater
Optimal cord clamping (also known as delayed or deferred cord clamping), provides the baby with its full volume of blood, important in helping the baby transition to life outside the womb. This is because at birth, the baby’s circulatory and respiratory systems need to make rapid changes to adapt to breathing air, circulating blood to the lungs for the first time. During pregnancy, up to half of the foetal blood circulates to the placenta - at birth this needs to quickly change so that around the same amount goes instead to the lungs. [3]
Immediate cord clamping can increase the risk of low blood volume and low blood pressure in the newborn baby and can, for example, decrease the amount of blood leaving the heart or going to the brain, with potentially serious consequences, possibly including brain damage.[3], [5], [6] With optimal cord clamping, the cord is left unclamped and the umbilical vein will continue to pulsate while this blood passes through to the baby; eventually the umbilical vein and arteries will empty of blood, giving a white appearance, then constrict and close physiologically, once the blood has been fully drained. As well as red blood cells, this blood contains stem cells, growth factors and other important components.[3],[5] The benefits of optimal cord clamping include improvements in several longer term outcomes, including increased blood iron levels and a reduced risk of anaemia several months after birth as well as improved neurodevelopmental outcomes.[3], [7], [8] For babies born early (preterm), clamping the umbilical cord straight away could mean depriving the baby of even more of its total blood volume - up to 50%.[3] So optimal cord clamping for these babies is especially important and there is evidence that it can reduce their chances of several complications including anaemia, serious infections, bleeding or needing blood transfusions, and likely reduces the risk of death.[3], [8], [9] One study found that babies born early have up to a 28% increased chance of survival with optimal cord clamping.[10] There were concerns that optimal cord clamping could increase the number of cases of neonatal jaundice severe enough to require treatment, however, the most recent research studies, including a Cochrane review, concluded that this is not the case.[3], [9]
Except where intense resuscitation is needed, The World Health Organisation, Royal College of Midwives, Royal College of Obstetricians and Gynaecologists and the National Institute for Health and Care Excellence all now advise waiting at least 1-3 minutes before clamping or cutting the cord.[8], [11], [12] Here at AIMS, we would also like practitioners to consider the physiological approach advocated by midwife Amanda Burleigh, who has been campaigning for optimal cord clamping to be widely implemented since 2005.[7], [13] Called Wait for White, her approach calls on practitioners to offer to wait until the umbilical cord is white and has stopped pulsating before clamping it (assuming the woman or birthing person hasn’t opted for not clamping the cord at all - lotus birth). This stage can be reached at different timepoints depending on the situation,[3], [13] so there is no ‘fixed time limit’ for when the cord should be cut and clamped in this approach.
Intact cord resuscitation allows healthcare professionals to begin resuscitation for babies who need this, without having to first clamp or cut the umbilical cord. Having the baby continue to receive this oxygen-rich cord blood can help to compensate for low oxygen levels in the baby’s blood and is linked to improved outcomes,[3], [4] In hospital settings, bedside resuscitation with specialist bedside resuscitaire equipment can facilitate this, although is not yet available everywhere.[14]

Resuscitation at homebirth keeping the cord intact (Hayden Trace)
Further Reading
[1] My Expert Midwife (2019) ‘What is delayed cord clamping?’: https://myexpertmidwife.com/blogs/my-expert-midwife/delayed-cord-clamping
[2] Raju, T. N. (2013) ‘Timing of umbilical cord clamping after birth for optimizing placental transfusion’, Current opinion in pediatrics, 25(2): 180-187 http://neonatologia.eu/files/publikacje/cordclamp.pdf
[3] Rabe, H., Mercer, J., & Erickson-Owens, D. (2022) ‘What does the evidence tell us? Revisiting optimal cord management at the time of birth’, European Journal of Pediatrics, 181(5): 1797-1807 https://pmc.ncbi.nlm.nih.gov/articles/PMC9056455
[4] Andersson, O., & Mercer, J. S. (2021) ‘Cord management of the term newborn’ Clinics in Perinatology, 48(3), 447-470. www.researchgate.net/publication/353755777_Cord_Management_of_the_Term_Newborn
[5] Mercer J, Bewley S. (2009) ‘Could early cord clamping harm neonatal stabilisation?’, Lancet, 374: 377–378 www.thelancet.com/journals/lancet/article/PIIS0140-6736(09)61410-0/fulltext
[6] Katheria, A. C., Lakshminrusimha, S., Rabe, H., McAdams, R., & Mercer, J. S. (2017) ‘Placental transfusion: a review’, Journal of Perinatology, 37(2): 105-111 www.nature.com/articles/jp2016151
[7] Wait for White (2025) ‘About Optimal Cord Clamping’ https://waitforwhite.com/about
[8] Rabe, H., Gyte, G. M., Díaz‐Rossello, J. L., & Duley, L. (2019). Effect of timing of umbilical cord clamping and other strategies to influence placental transfusion at preterm birth on maternal and infant outcomes. Cochrane Database of Systematic Reviews, (9). https://pubmed.ncbi.nlm.nih.gov/31529790
[9] Robledo, K. P., Tarnow-Mordi, W. O., Rieger, I., Suresh, P., Martin, A., Yeung, C., ... & Bowen, J. (2022).Effects of delayed versus immediate umbilical cord clamping in reducing death or major disability at 2 years corrected age among very preterm infants (APTS): a multicentre, randomised clinical trial. The Lancet Child & Adolescent Health, 6(3), 150-157. www.healthynewbornnetwork.org/hnn-content/uploads/Effects-of-delayed-umbilical-cord-clamping.pdf
[10] Fogarty, M., Osborn, D. A., Askie, L., Seidler, A. L., Hunter, K., Lui, K., ... & Tarnow-Mordi, W. (2018). Delayed vs early umbilical cord clamping for preterm infants: a systematic review and meta-analysis. American journal of obstetrics and gynecology, 218(1), 1-18. https://ses.library.usyd.edu.au/bitstream/handle/2123/24724/1-s2.0-S0002937817314394-main.pdf?sequence=1&isAllowed=y
[11] Word Health Organisation (2014)’ Delayed Umbilical Cord Clamping for Improved Maternal and Infant Health and Nutrition Outcomes’ www.ncbi.nlm.nih.gov/books/NBK310522
[12] National Institute for Health and Care Excellence (2023) ‘Intrapartum care’: www.nice.org.uk/guidance/ng235/resources/intrapartum-care-pdf-66143897812933
[13] Burleigh, A. and Uwins, C. (2018) Campaigning for Change: Implementing Optimal Cord Clamping, The Practising Midwife Volume 21 Issue 2, retrieved online https://doi.org/10.55975/RABJ2085
[14] Burleigh, A. (2020) ‘Intact Cord Resuscitation’: https://waitforwhite.com/intact-cord-resuscitation
Please feel free to download and share a pdf of this article. If you wish to use AIMS copyright material please see aims.org.uk/general/aims-copyright
If you found this article helpful please consider becoming an AIMS member or making a donation to support our work. We are a small charity that accepts no commercial sponsorship, in order to preserve our reputation for providing impartial, evidence-based information.
AIMS supports all maternity service users to navigate the system as it exists, and campaigns for a system which truly meets the needs of all.